Properties (15)
- purpleRed
- A symptom network model of misophonia
- (Andermane et al., 2023b)
A symptom network model of misophonia: From heightened sensory sensitivity to clinical comorbidity
Status:: #status/Bare-bones-review
Metadata
- Item Type: #journalArticle
- Authors:: Nora Andermane, Mathilde Bauer, Julia Simner, Jamie Ward,
- Date Added: October 1, 2025
- URL: https://onlinelibrary.wiley.com/doi/10.1002/jclp.23552
- DOI: 10.1002/jclp.23552
- Cite Key: andermaneSymptomNetworkModel2023
- Tags:: #Misophonia, #comorbidity, #anxiety, #sensory-sensitivity, #interoception, #network-model,
- PDF Attachments
Abstract
| Background/Purpose | Background- • Misophonia is a disorder of decreased tolerance to specific sounds (triggers); triggers often human-made mouth noises, repetitive noises, or animal/inanimate object sounds • Emotional reactions include anger, disgust, anxiety, powerlessness; physiological responses (increased heart rate, sweating, wish to escape) consistent with fight-or-flight • Thought to be relatively common; a German representative sample reported what they described as clinically significant misophonia in a minority of cases • Often comorbid with generalized anxiety, autism, obsessive-compulsive personality traits • Profiling studies characterize misophonia but lack a mechanistic account of how/why features co-occur • Mental disorders currently regarded as emerging from simpler interacting elements prevalent in the general population and shared across disorders (transdiagnostic) • RDoC framework treats contributing factors as interacting "domains" • Network approach models disorders as symptoms (nodes) forming inter-connected hubs; comorbidities arise because symptoms/domains are shared between hubs • Previously applied to PTSD, bipolar disorder, psychosis; applied here to misophonia for the first time • Candidate domains for misophonia: interoception (and/or physiological reactivity), sensory sensitivity, social-emotional cognition • May resemble a family of related conditions sharing the trait of sensitivity: hyperacusis, autism, migraine Purpose- • Test the hypothesis that misophonia co-occurs with autistic traits, anxiety, migraines, obsessive-compulsive traits, and other hearing-related conditions • Test whether misophonia is directly related to heightened sensory sensitivity • Stratify the sample into subgroups beyond a simple presence/absence dichotomy • Model misophonia facets within a symptom network to understand links to sensory sensitivities and clinical symptoms - |
| Participants/samples | • Combined sample N = 1430; all completed Part 1; subgroup N = 419 completed Part 2 • Two-part online study; recruited from sources favoring misophonics (BBC radio interview; N = 1158 after exclusions) or non-misophonics (student body, acquaintances, online panel; N = 272 after exclusions) • Group assignment based on cluster analysis of SMS factor scores, not recruitment stream • Three groups: non-misophonic, moderate misophonic, severe misophonic • Part 1 group Ns: non-misophonic 367; moderate 643; severe 420 • Part 2 group Ns: non-misophonic 196; moderate 113; severe 110 • Inclusion: aged 18–70; self-reported normal or corrected-to-normal vision and hearing • Part 2 exclusions: epilepsy (Pattern Glare criterion); substantially incomplete responses; unfeasibly fast responses; duplicate attempts • Small amount of missing data (pattern glare, auditory sensory sensitivity task) • Preregistered; approved by University of Sussex ethics committee |
| Measures | • Hearing Questionnaire – descriptions of migraine phonophobia, phonophobia, misophonia, hyperacusis, tinnitus, hearing difficulties; rated on a 4-point scale; plus help-seeking (Yes/No) • Sussex Misophonia Scale (SMS) – two-part; Part 1 elicits triggers, Part 2 Likert questions on associated experiences; five factors (feelings/isolation, life consequences, inter-social reactivity, avoidance/repulsion, pain) • Phenomenological Responses to Sounds – multivariate profile across 17 descriptors to 32 sound clips (written up as a separate study) • AQ (Autism Spectrum Quotient) – 50-item; five subscales (attention switching, attention to detail, communication, imagination, social skill) • GSQ (Glasgow Sensory Questionnaire) – 42-item; seven sense domains; half items hyper-sensitivity, half hypo-sensitivity • ASI-3 (Anxiety Sensitivity Index) – 18-item; three subscales (Cognitive, Physical, Social) • MAIA – 32-item; interoceptive abilities/bodily awareness; eight subscales • OCI (Obsessive-Compulsive Inventory) – 42-item; seven subscales (Checking, Washing, Obsessing, Mental Neutralizing, Ordering, Hoarding, Doubting) • POEM (Penn Online Evaluation of Migraines) – branching-logic questionnaire; classifies into seven headache categories • Pattern Glare task – visual sensitivity; black/white parallel lines at low/middle/high spatial frequencies; rated on descriptors; two factors (Visual Distortions, Somatic Discomfort) |
| Procedures | • Part 1: Hearing Questionnaire and SMS; all other measures in Part 2 • Conducted online; tasks hosted on the authors' own website • Questionnaire items required forced response; Phenomenological Responses to Sounds and Pattern Glare descriptors used a Visual Analog Scale • Part 2 required a computer screen and ideally headphones • Pattern Glare: gratings viewed for 12 s then rated; virtual chinrest calibration via blind spot; low spatial frequency included as a sanity check • Analysis: two-step cluster analysis (hierarchical Ward's method then k-means) on z-scored SMS factors; continuous measures analyzed as mixed linear models with post hoc ANOVAs and corrected comparisons; categorical headache data via chi-square; Bayes factors and FDR correction applied • Symptom network: Gaussian Graphical Model over 31 nodes; graphical LASSO regularization; bootstrapped stability analysis |
| Results | Cluster analysis • Three-group solution generated groups low, medium, and high across all five SMS factors • Subgroups defined by overall severity, not by distinct factor profiles; no double or simple dissociations among factors • Same severity-based grouping found when extracting four groups and when combining highly correlated factors • Moderate and severe groups largely met the diagnostic threshold and self-reported misophonia; non-misophonic group did not • Groups did not differ by gender; misophonic groups tended to be older Hearing questionnaire • Three groups differed on all hearing-related conditions • Most differences between non-misophonics and the other groups; moderate vs. severe differed for hyperacusis and phonophobia • Professional help-seeking low overall but differed across groups; greater in severe than moderate Clinical comorbidities • AQ: group effect present; all three groups differed on attention-to-detail; social and communication differences driven by the severe group; attention switching and imagination not linked to group differences • ASI-3: severe misophonics differed from moderate and non-misophonics; the latter two did not differ • OCI: group differences in washing, checking, obsessing, ordering, doubting driven by severe vs. non-misophonics; severe vs. moderate differed for checking and ordering; moderate did not differ from non-misophonics • POEM: severe group more likely to experience migraine with aura and less likely to have mild non-migrainous headache; severe differed from non-misophonics; moderate did not differ from either group Sensory sensitivity • GSQ overall: group difference driven by severe misophonics; other two groups did not differ • GSQ hypersensitivity: severe differed from non-misophonics across all modalities; moderate differed from non-misophonics on auditory and olfactory; moderate differed from severe across all modalities • GSQ hyposensitivity: group difference; higher for severe relative to moderate • MAIA (interoception): no group effect; contrasts with differences observed for exteroceptive senses • Pattern Glare: severe group gave higher ratings at mid and high spatial frequencies; no group difference at low spatial frequency Symptom network • GSQ (sensory sensitivity) occupied a key position on all centrality measures; maintained when split into hyper/hypo variables • Among SMS subscales, Pain had the highest bridge and betweenness centrality • Strongest SMS–AQ link was to attention-to-detail • Comorbidities linked to misophonia primarily via sensory-attentional symptoms that are themselves transdiagnostic; social-based symptoms did not form a central clique • Network stable under bootstrap resampling; GSQ remained central after removing auditory items • Bridge symptom linking misophonia to the network shifted from Avoidance (non-misophonics) to Pain (misophonics and combined sample) Bayes factors • Moderate vs. non-misophonics: sensitive rejections of the null for AQ attention-to-detail and GSQ hypersensitivity; most other results sensitive nulls • Severe vs. non-misophonics: sensitive rejections across multiple AQ, GSQ, ASI, OCI, and Pattern Glare variables |
| Discussion/Limits | Conclusion- • Cluster analysis yielded three groups distinguished by severity, not distinct factor profiles; three discrete groupings despite prior work noting misophonia's continuous nature • Comorbidities linked to misophonia severity rather than misophonia status per se; not a primary cause but may drive transition to a more severe profile • Moderate group resembles non-misophonics on most measures and did not differ on clinical traits, but differs in attention-to-detail, auditory/olfactory hypersensitivity, and hearing comorbidities (e.g., hyperacusis) • Attention-to-detail is the one trait distinguishing both misophonic groups, unusual in relating to a cognitive ability rather than a problem/deficit • Severe misophonics differ from moderates in breadth of triggers, broader sensory sensitivities, elevated clinical traits, greater migraine tendency, and other hearing-related issues • Sensory sensitivity is the main bridge between misophonia and clinical symptoms, including but not limited to auditory; elevated sensitivity and associated pain-like experiences may be the primary cause of the severe group's aversive effects on mental health and life • Increased sensory sensitivity may drive pain and affective dysregulation corresponding to anxiety and other clinical traits; exact mechanism not yet fully explained • Misophonia and migraine-with-aura link shown for the first time; migraine and pattern glare share a putative mechanism of increased cortical excitability • Interoceptive awareness (MAIA) not strongly related to misophonia • Network is not causal; closer, stronger connections have greater mutual influence |
| Limitations:: | • The network is not a causal model and cannot establish that misophonia causes comorbidities or vice versa • Sensory sensitivity may cease to be central if other important but presently omitted symptoms are added • Interoception assessed only via the self-report MAIA |
| Future Directions:: | • Alternative measures of interoception may be more strongly related to misophonia • The production of autonomic responses to sounds, rather than the ability to sense them, may be the atypical process in misophonia |
| Relevance:: | • looked describe the perceptual, affective, and cognitive profile of Misophonics • study used cluster analysis on a large ( N= 1430) sample of questionnaire data and found two subgroups of Misophonics with differing severity. • a subset (419) completed additional tests and showed that those with worse Misophonia had worse clinical symptoms of comorbidities • high Misophonia group also showed enhanced attention to detail and hypersensitivity across multiple modalities • showed a novel symptom network model of Misophonia linking it to other conditions. |
Notes
key terms and concepts
-
Misophonia – a disorder of decreased tolerance to specific sounds, referred to as triggers.
-
Triggers – specific sounds, often human-made noises originating from the mouth (lip-smacking, crunching, chewing, breathing), repetitive noises, or sounds made by animals/inanimate objects.
-
Transdiagnostic – shared with other disorders; traits that are, to some degree, prevalent within the general population and shared by other disorders.
-
Interoception – our ability to detect and interpret signals from the body (heart, viscera, etc.); divisible into further domains (e.g., interoceptive accuracy v. interoceptive awareness).
-
Sensory sensitivity – our responsiveness to the exteroceptive world (responses to lights, sounds, tastes, odors); classifiable as hyper-sensitivity (over-responsiveness) or hypo-sensitivity (under-responsiveness).
-
Symptom network model – a mathematical modeling approach regarding mental disorders as a network of symptoms (nodes) connected by edges (partial correlations).
-
Hub – an inter-connected set of symptoms that interact with each other; may approximate traditional multi-symptom diagnostic categories.
-
RDoC (Research Domain Criteria) – a framework treating any contributing factor as interacting elements termed "domains."
-
Degree centrality – sums all connection strengths emanating from each symptom (ignoring sign).
-
Bridge centrality – degree centrality restricted to weights between (not within) different measures.
-
Betweenness centrality – the extent to which a node serves as a bridge on shortest paths between other nodes.
my engagement notes
my questions
my comments
Bookmarks
- Symptom network modeling (page 18)
reading notes
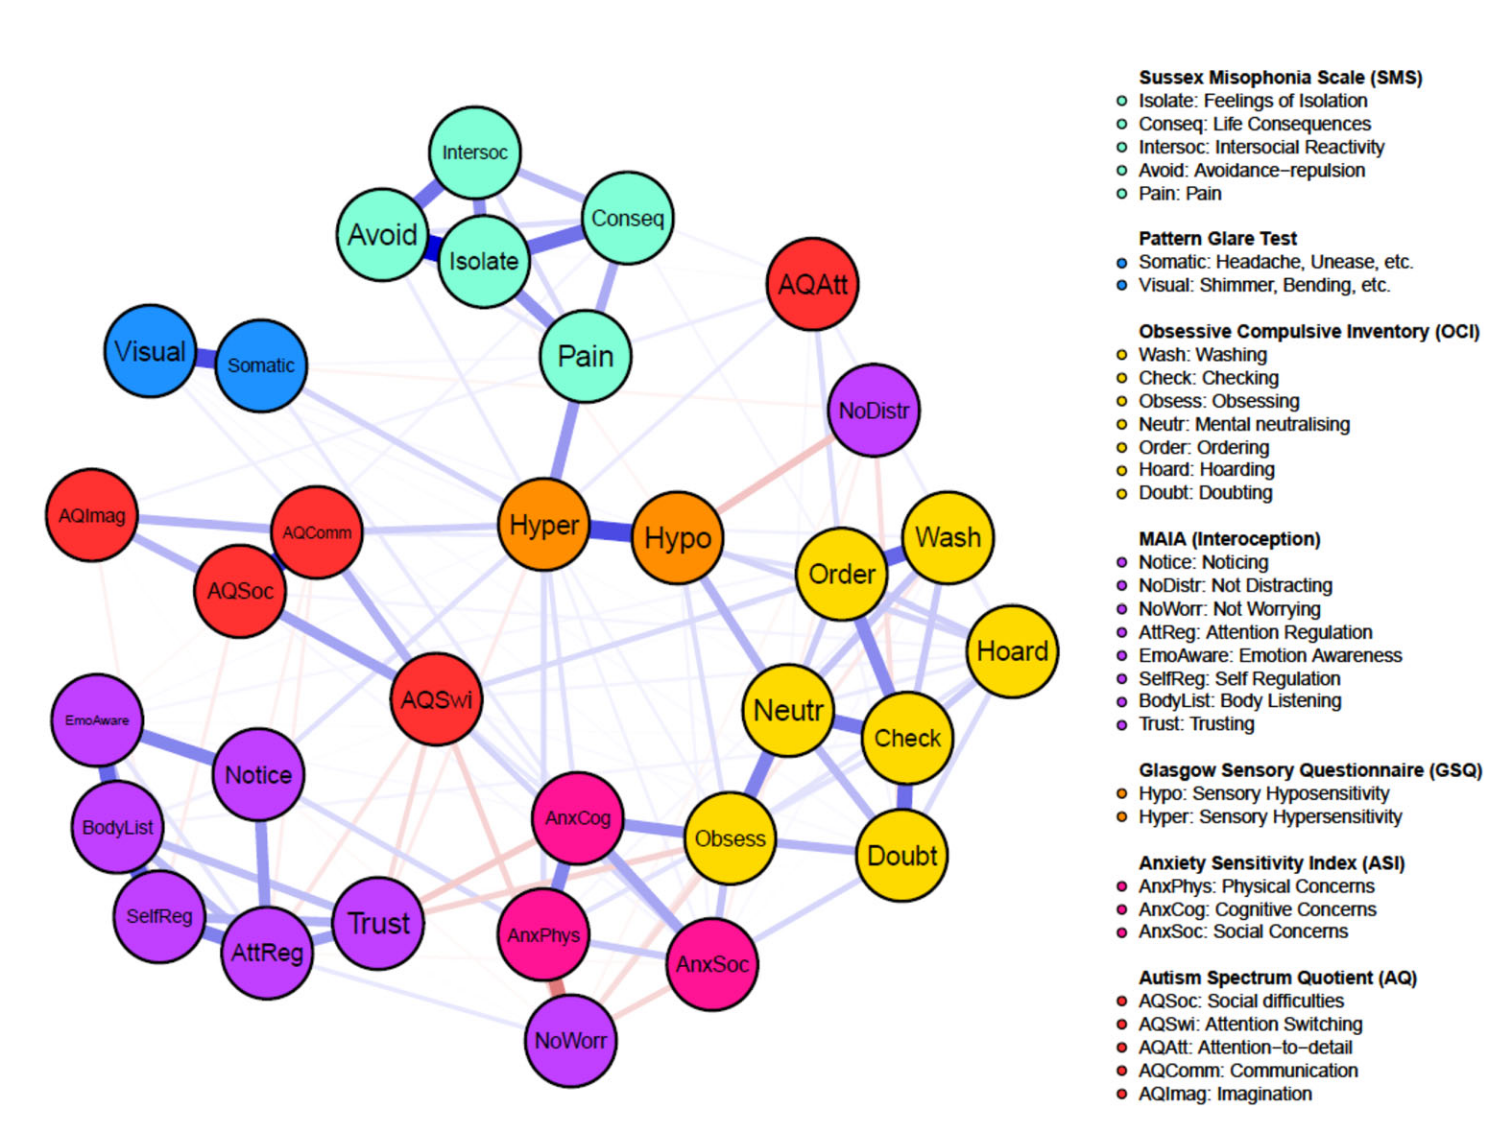
contextual statement
In a 2023 study, Andermane attempted to characterize the perceptual, affective, and cognitive profile of misophonia and its links to sensory sensitivity and clinical comorbidity by administering a battery of misophonia, sensory, and clinical measures (SMS, AQ, GSQ, ASI-3, MAIA, OCI, POEM, Pattern Glare) to a large online sample (N = 1430; Part 2 subset N = 419) and applying cluster analysis and symptom network modeling.
summary statement
In a 2023 study, Andermane characterized misophonia subgroups and their comorbidities by administering misophonia, sensory sensitivity, and clinical measures to a large online sample and applying cluster analysis and symptom network modeling. They found three groups differing in misophonia severity rather than factor profile, with clinical comorbidities (autistic traits, anxiety sensitivity, obsessive-compulsive traits, migraine with aura) largely limited to the severe group and sensory sensitivity occupying a central position in the symptom network. From this they concluded that the core features of misophonia are sensory-attentional in nature, with severity strongly linked to transdiagnostic comorbidities via sensory sensitivity.
Zettelkasten
-
moderate Misophonics often lacking comorbidities is dispositive of comorbidities as a cause
-
symptom network model showing some symptoms and traits are more or less connected to Misophonia
-
sensory sensitivity as a the bridge between Misophonia and other conditions
-
Study gives evidence misophonia is linked to visual sensitivity, at least in severe cases
-
symptom network model showing some symptoms and traits are more or less connected to Misophonia